
Vancouver’s Healthcare Marketing Problem Is Not Your Budget. It’s Your Brief.
IntroductionThe ads are running. The landing page is live. And the clinic manager just received a formal inquiry from the College of Physicians and Surgeons of British Columbia about a comparative claim in the ad copy. This is the exact moment a Vancouver medical practice realizes generalist marketing has turned from a cost-saving tactic into an existential liability.
In a metro area of 2,642,825 people, the opportunity for patient acquisition is real. So is the regulatory density. Vancouver is not a city where you can spin up a Google Ads account, target 'Botox near me,' and hope the College stays asleep.
The CPSBC enforces advertising standards that ban comparative superlatives and patient endorsements. PIPEDA and BC's Personal Information Protection Act (PIPA) sit atop every form, every tracking pixel, and every retargeting script. Add in Canada's Anti-Spam Legislation (CASL), and the compliance surface is practically a second full-time job.
The wrong way to decide is on cost alone. Marketing for a Vancouver clinic demands the compliance framework first, the creative second. The agency you pick is either wired for that reality or it is building a compliance time bomb inside your campaign. This is the argument for a healthcare marketing agency equipped to audit risk before chasing volume.
Key Takeaways
What a practice owner or US-based marketing director needs to carry forward:
- The compliance moat is real: CPSBC actively reviews complaints on ad copy; generalists who skip pre-publication review trigger audits that cost far more than a specialist retainer ever would.
- Specialist pricing lines up: US specialist retainers commonly run $1,500 to $6,000 per month, comparable to capable generalists, but the specialist bundle includes regulatory guardrails a generalist won't even know are missing.
- The 6-to-8-week reveal: Switching from a generalist to a specialist typically surfaces the difference within two months, mostly in the form of things that stop going wrong: ads that serve without disapprovals, tracking that reports appointments instead of impressions, and creative that gets cleared on the first submission.
- Multilingual is no longer optional: More than one in four people in Vancouver speak a non-official language at home, with Mandarin leading; agencies that cannot produce and compliantly review multilingual PPC are leaving a material patient pool untouched.
- AI is the 2026 moment: Over 80% of marketing and medical affairs teams are already working with or considering AI, but in Vancouver the killer app is compliance auditing that scans pre-launch creative for CPSBC violations, a capability general agencies have zero exposure to.
- Vetting must be jurisdictional: US-based healthcare groups hiring remotely must script questions about PIPEDA meaningful consent, CASL express consent, and cross-border data hosting; a 'yes we do healthcare' answer is insufficient when BC privacy law is the operating standard.
What a Healthcare Marketing Agency Does That a Generalist Can't

A generalist builds a Google Ad. A healthcare specialist builds a campaign that survives a College complaint. The difference shows up across copy, consent, and channel selection, and it is structural, not stylistic.
The first gap is the pre-publication review habit. The College of Physicians and Surgeons of British Columbia prohibits advertising that is false, misleading, or uses comparative superlatives and patient endorsements. A generalist will write ad copy that sounds compelling.
A specialist reads every line against the CPSBC standard as a reflex. Practices that switch learn this fast: the shift isn't felt in more clicks. It's felt in ads that serve without disapprovals and in a compliance file already built before the campaign launched.
Then there's consent architecture. BC's PIPA bars collecting, using, or disclosing personal information without consent, and specifically states that consent obtained through false or misleading information is not validly given. A generalist drops a standard cookie banner and a generic Mailchimp pop-up.
A specialist builds the disclosure layer so that consent is informed and documentable: every form, every phone call tracker, every retargeting pixel gets mapped against CASL's express consent rules. Without this, a clinic isn't marketing. It's generating a chain of privacy breaches dressed as leads.
The channel gap is equally sharp. Google and Meta treat health advertisers as a special class: restricted categories, certification requirements, prohibited claims, and a hard ban on personalizing ads by health condition. A generalist who has optimized an ecommerce account will learn these restrictions when the ad disapprovals hit.
A specialist built the campaign inside those guardrails from day zero. The specialist also knows what 'good' costs in a given specialty. The generalist has no reference point and can burn six months of budget discovering that cost per booked appointment in dermatology is structurally different from cost per click in orthodontics.
The problem is that general agencies underestimate the complexity baked into the healthcare brief. Healthcare marketing specialists balance opportunity with responsibility, applying judgment from exposure to multiple clinical organizations rather than guessing at it.
A generalist agency that tries to absorb this on the fly does not just waste money. It makes the clinic's medical director the de facto compliance reviewer, a dangerously misplaced pressure point.
The Vancouver Regulatory Moat: CPSBC, PIPEDA, and a US-Canada Compliance Comparison
If you are a US-based healthcare marketer hiring a Vancouver agency, unlearn HIPAA. HIPAA does not map cleanly onto the two Canadian privacy statutes that campaigns routed through Vancouver must satisfy. PIPEDA is the federal privacy law covering private-sector organizations.
BC's PIPA adds a provincial floor that is more restrictive. PIPA gates every stage of personal information processing, collect, use, disclose, behind consent.
And PIPA declares consent invalid if it was obtained through false or misleading information. That converts a slightly aggressive landing page offer into a legal risk in a way HIPAA's transaction-based disclosures do not.
Then comes the CPSBC, which adds a regulatory layer with no real HIPAA parallel. In the US, FDA and FTC oversight governs healthcare advertising. In British Columbia, the provincial college holds jurisdiction over how a physician markets their practice.
The CPSBC can investigate an ad, demand a rewrite, and impose disciplinary measures. Their advertising standards prohibit comparative superlatives ("best plastic surgeon in Vancouver") and patient testimonials that imply clinical outcomes. Any advertising that the College views as undermining the dignity of the profession is also banned.
The US-based marketer's instinct is to run an aggressive campaign anchored on social proof: patient stories, before-and-after imagery, competitor comparison tables. In Vancouver, those instincts will produce a College complaint. The European-style privacy framework embedded in PIPEDA and PIPA restricts cross-border transfer of patient data in ways a standard US martech stack may violate by default. Think US-hosted CRM, US-hosted analytics, US-hosted email automation.
A US health network entering the Vancouver market has to stop using its home regulatory playbook as the reference standard. The CPSBC and PIPA combination creates a compliance moat navigable only by an agency whose workflows are built on pre-clearance, express consent documentation, and Canadian-hosted data infrastructure.
High-ROI Channels for Vancouver Clinics: From Kitsilano SEO to Multilingual PPC
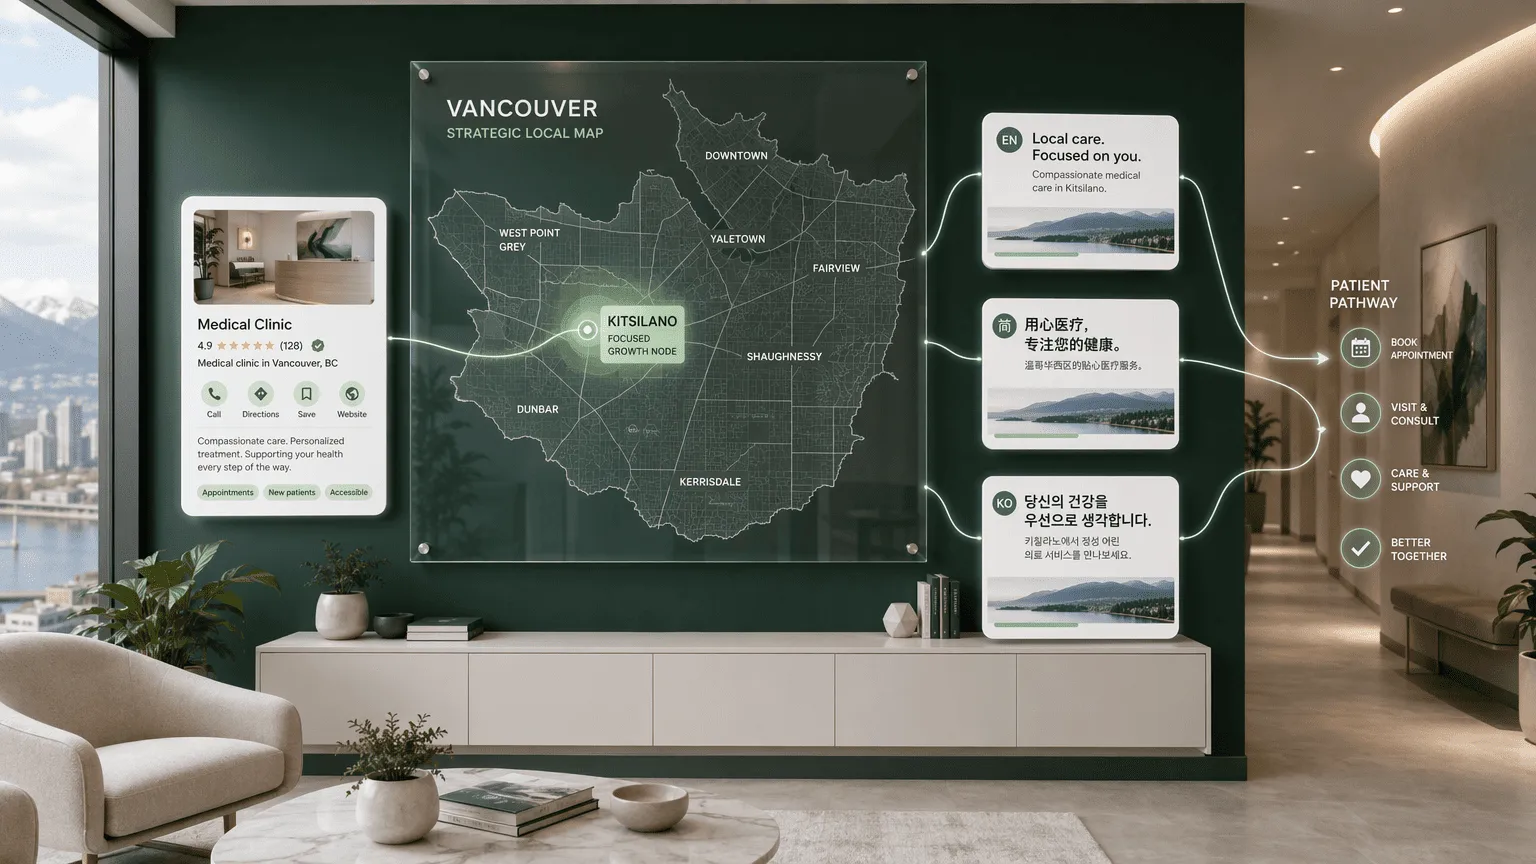
The highest-performing channel for a Vancouver clinic is the one that reflects where patients search and what they search for in their own language, framed inside Google's local ranking signals. For most clinics, that points to two investments: neighborhood-level SEO and multilingual PPC.
Local intent drives conversion. A patient searching 'Kitsilano physio' has made a geographic decision. An optimized Google Business Profile that surfaces for that query, supported by location pages that load fast and carry the right structured data, captures intent that general keyword campaigns miss. This is where technical SEO directly feeds the patient pipeline: Core Web Vitals thresholds (2.5 seconds or less for Largest Contentful Paint, 200 milliseconds or less for Interaction to Next Paint, and 0.1 or less for Cumulative Layout Shift, assessed at the 75th percentile) determine whether the page actually ranks against competitors who are just as local. You need a loading profile that satisfies Google's machine and a content profile that answers the query without triggering CPSBC claims risk.
Then add the language layer. In Vancouver, Mandarin is the main non-official language spoken at home. More than one in four people predominantly speak a non-official language at home.
An English-only campaign makes you invisible to a large portion of the patient base. A multilingual PPC campaign runs compliant Mandarin and Punjabi ad copy that opens a dedicated, pre-vetted landing page. The content on that page must still clear CPSBC standards, so the translation requires supervised adaptation that aligns clinical accuracy with regulatory wording.
The landing page itself needs to do more than convert. It needs to anticipate a College review. That means no patient outcome claims, no unsubstantiated efficacy language, and no before-and-after clinic photography that implies procedure results. A specialist agency builds these pages inside a template that enforces compliance while optimizing for conversion. The result: local ads in the languages Vancouver actually speaks, served through compliant infrastructure that will survive a complaint review.
The 2026 AI Inflection: How Predictive Engagement Is Reshaping Vancouver Medical Marketing

By the middle of 2026, the dominant AI conversation in healthcare marketing has shifted from content generation to predictive compliance and personalized channel routing. The tools now exist to scan a campaign's entire creative library against CPSBC language standards before a single ad goes live, and the agencies that are adopting this capability are compressing what was previously a week-long manual legal review into a same-day pass-fail audit.
Predictive AI is also changing patient acquisition economics for elective and cash-pay procedures. AI-powered Next Best Action systems now enable real-time channel and content decisions based on patient-specific behavioral data, routing the right offer through the right communication channel. In a Vancouver context, this means a patient who has repeatedly searched for Botox in Mandarin on mobile gets routed a Mandarin-language SMS or WeChat message that is pre-approved and configured to book directly. The lift is significant: personalized calls-to-action drive more than double the engagement of generic ones.
Compliance auditing is the AI application that matters most to a Vancouver clinic operator, however. AI tools now ingest the CPSBC's guidance documents and then scan ad copy, landing pages, and chatbot scripts for prohibited language patterns: superlatives, implied outcome claims, and testimonial-style phrasing. This is automated pre-publication review, and it closes the gap between what an agency intends to publish and what the College could flag. A generalist agency cannot build this layer because they do not have the corpus of regulatory decisions and complaint precedents to feed the model.
The CPSBC's stance on autonomous AI, like patient-facing chatbots, is still evolving, but the direction of travel is clear: any AI-generated content that carries medical information is viewed by the College as a publication of the practitioner, and the liability sits with the clinic regardless of the tool chain. Messages delivered within clinical workflows drive much higher engagement than the same content served through traditional digital channels, but only if the compliance wrapper is already proven. In 2026, the agency's role is to make AI output defensible and scalable.
A US Marketer's Vetting Guide: Red Flags, Remote Risks, and Must-Ask Questions for Vancouver Agencies

If you're a US-based healthcare network hiring remotely into Vancouver, your vetting must be jurisdiction-specific. Do not accept 'yes we understand healthcare' as a satisfactory answer. The following five questions will surface whether you're talking to a specialist or a generalist who is about to learn Canadian privacy law on your clinic's dollar.
- Walk me through your pre-publication review process for CPSBC compliance: The agency should describe a checklist based on the College's advertising standards, including automated or manual scans for comparative claims, patient testimonials, and misleading inferential language. If they cannot reference the CPSBC by name and describe its complaint investigation powers, end the call.
- How do you obtain and document meaningful consent under PIPEDA and PIPA? Look for a description of consent types (express versus implied), a clear statement on when each applies under CASL, and evidence that consent strings are stored and auditable. A blank look or a pivot to 'HIPAA authorization forms' means they are applying US law to Canadian operations.
- Where is the patient data hosted, and how are cross-border transfers managed? PIPA scrutinizes personal information leaving Canada. The agency must describe a Canadian-hosted or legally equivalent data stack, with contractual safeguards for any US-based subprocessors. If your martech stack relies on a US-hosted analytics suite, expect the agency to flag this and propose a compliant architecture.
- Can you produce a CPSBC-compliant multilingual campaign in Mandarin and Punjabi, and show me the translation review layer? The right answer is a documented process in which a medically fluent translator renders the copy, and then a compliance editor verifies that the translation does not introduce prohibited claims. Automated machine translation with no human oversight is a violation waiting to happen.
- What was the last CPSBC advertising complaint you managed, and what was the resolution? A silent pause or a deflection tells you they have never been stressed-tested against College enforcement. A specialist will have an anonymized case to describe, from complaint receipt through College response and remedial rewrite. The answer calibrates their real-world regulatory fluency.
Pricing Realities: What a Specialized Vancouver Healthcare Agency Actually Costs in 2026
$1,500 consistently shows up as the floor because below that threshold the compliance infrastructure cannot be sustainably built into the retainer. Above it, the range reflects scope: multilingual asset production, dedicated CPSBC compliance review, and the data residency measures that PIPA mandates push the retainer ceiling toward $6,000 per month.
| Cost Driver | Generalist Agency | Healthcare Specialist Agency |
|---|---|---|
| Monthly Retainer Range | $1,200 to $4,500 | $1,500, $6,000 |
| CPSBC Pre-Publication Review | Not included; demand it and the brief gets delayed indefinitely | Standard operating procedure; baked into creative production timelines |
| Multilingual PPC Management | Rarely offered in-house; outsourced translation with no compliance overlay | Managed internally; copy adapted and audited for regulatory adherence in Mandarin and Punjabi |
| Consent & Data Residency Setup | Cookie banners only; no PIPA audit | Express consent documentation layer, CASL-compliant email triggers, and Canadian-hosted analytics infrastructure |
| Compliance Remediation Cost | Variable and unbounded; one College complaint can trigger a full campaign suspension and legal consultation | Mitigated by the agency's pre-launch audit; typical remediation is a same-day rewrite, not a crisis |
The specialist retainer may look higher upfront. A generalist agency that draws a CPSBC complaint generates costs that are entirely unbudgeted: campaign pause, copy rewrite, possible legal consultation with BC health lawyers, and the reputational damage of a public College inquiry. A healthcare specialist's efficiency, accuracy, and minimized risk often produce better long-term value. You are paying for pre-emption here, not just production.
Clinads and the Vancouver Agency Landscape: A Comparative Snapshot

Clinads built its entire platform around a single problem: clinics lose patient acquisition volume because their infrastructure stays invisible to the surfaces where patients now search. Google's AI overviews, ChatGPT, Gemini, Perplexity. Those are the new front doors. The brand runs a AI-first growth platform with software starting at $399 per month for the marketing engine and a done-for-you SEO and GEO layer for clinics that want execution alongside the tech. The differentiator is vertical integration: Clinads produces the creative, audits it for regulatory compliance, and simultaneously pushes structured content into the AI surfaces that generic retainer models ignore.
Vancouver's competitive landscape also includes firms like ICG (ichelonconsulting.com), which pitches creative storytelling and digital strategy across multiple verticals, and Pulse Digital, which has built a content library specifically around CPSBC and PIPA requirements for Vancouver clinics. The headline difference is depth of compliance tooling versus breadth of service. A multi-vertical agency offers email, web, and paid media.
A healthcare-dedicated firm offers those same channels plus an embedded regulatory audit that runs before every launch. For a clinic whose next campaign cycle absolutely cannot trigger a College inquiry, that embedded audit is the line between marketing and liability.
Practices that switch to a specialist typically see the improvement within six to eight weeks. The difference comes from having the compliance machinery already installed, not from sharper creative.
Conclusion
Vancouver's regulatory density and demographic shape have turned healthcare marketing into a concentrated set of legal-technical requirements that generalist briefs cannot satisfy. The cost of running an unguarded campaign is now measured in College complaints, canceled ad accounts, and privacy breaches that a general agency won't catch until Patient Privacy asks for the consent logs. A CPSBC-compliant, PIPA-aware agency that creates campaigns in Mandarin and Punjabi is the configuration that works without back-drafting risk onto the clinic's medical director. The 2026 advice is straightforward: audit your agency for regulatory fluency first, then measure their creative output.
Frequently Asked Questions
What does a healthcare marketing agency do that a general marketing agency cannot?
A healthcare agency enforces three key compliance practices:
- Runs every ad, landing page, and email through a pre-publication compliance review aligned to CPSBC advertising standards.
- Documents meaningful consent under CASL and PIPA.
- Avoids claims that trigger provincial college audits and understands specialty-specific cost per booked appointment benchmarks.
How do Canadian healthcare privacy laws like PIPEDA and provincial regulations affect digital marketing for clinics in Vancouver?
PIPEDA and BC's PIPA require express, informed consent before collecting or using personal information. CASL layers email consent. Combined, they mandate that every form, tracker, and retargeting script on a clinic's digital properties is disclosed, consented to, and auditable, changing campaign architecture from the ground up.
Which marketing channels deliver the highest patient acquisition ROI for medical practices in Vancouver right now?
Neighborhood-level local SEO paired with Google Business Profile optimization and multilingual PPC (Mandarin and Punjabi) drive the highest returns. These channels capture high-intent, geographically filtered searches in the languages that a significant portion of Metro Vancouver actually speaks at home.
What should a healthcare provider in Vancouver look for when hiring a specialized agency, and how are results measured?
When evaluating an agency, ask these four questions and track one metric:
- Ask for their CPSBC pre-publication review process.
- Ask for their consent documentation workflow.
- Ask for their experience managing a College advertising complaint.
- Measure booked appointments tracked through dynamic number insertion and CRM integration, not clicks or impressions, and set the expectation that compliant infrastructure is a core deliverable.
What are the typical costs or pricing models for a healthcare marketing agency in Vancouver?
Specialist retainers run roughly $1,500 to $6,000 per month depending on scope, multilingual requirements, and depth of compliance review. Performance-based models are emerging but the fixed retainer remains the standard because it funds the regulatory audit layer that prevents unbudgeted College-complaint costs.
How is AI transforming patient engagement and medical marketing strategy in 2026?
AI now automates pre-publication CPSBC compliance audits on ad copy and landing pages. Predictive routing sends the right multilingual content through the right channel based on patient behavior, and the risk has shifted: liability for AI-generated medical information sits with the clinic, making a compliance-aware agency key.
Sources
- SEO & GEO Expert | Careers at ClinAds - getclinads.com
- Vancouver Healthcare Marketing Agency For Clinic Growth - pulsedigital.health
- Medical Marketing Agency vs General Agency · Medical Marketing - medicalmarketing.digital
- Specialist vs. General Agency in Healthcare Marketing - healthcaresuccess.com
Want help executing this for your clinic?
Book a 30-minute call and we will map what a real ad engine would look like for your specific service mix.
Book a call