
The AI Has Already Rewritten Medical Search. Most Practices Are Still Drafting the Old Playbook.
IntroductionYour practice's ranking report still shows keyword gains, but the phone is strangely quiet. This is the quiet crisis of AI-mediated search. AI Overviews now surface in 39.4% of U.S. desktop Google searches (Comscore data, June 2026), synthesizing answers that often keep the patient from ever clicking. The old medical SEO playbook, built on ten blue links and a map pack, fails when a generated summary decides which providers to name.
The problem is not that your page ranks. The problem is that generative AI chooses a different source to cite. For healthcare practices, this shift carries a specialized performance requirement that leaves no room for negotiation. AI systems strip away the middle layers of the local search funnel. Self-published content, service pages, and traditional content marketing become structurally disadvantaged unless intentionally redesigned for answer engines.
Key Takeaways
The AI-driven patient acquisition landscape now demands a structural overhaul. Here are the five realities every practice owner and healthcare marketer must operationalize today:
- Citation economy reality: 82% of AI citations for commercial medical prompts come from third-party sources, while owned pages capture just 3%. Your strategy must prioritize external citation cultivation over owned-page tweaks.
- Verification is mandatory: Google’s E-E-A-T and YMYL frameworks subject medical content to the highest trust scrutiny. Without explicit, entity-level verification signals, your practice remains invisible to AI synthesizers regardless of domain authority.
- HIPAA-safe content architecture works: You can build AI-friendly content without risking PHI exposure. An architecture that separates public educational content from protected transactional touchpoints resolves this tension entirely, and the formats are knowable.
- Reputation is an AI signal: Reviews, directory profiles, and structured sentiment data now directly dictate whether an AI Overview recommends your practice in the local answer box.
- Compliance now covers AI surfaces: State medical board rules and Google’s Scaled Abuse Forensics Examiner (SAFE) system jointly govern AI-visible content, criminalizing unsubstantiated claims, unearned specialization language, and fabricated testimonials with overlapping penalties.
The New Lexicon of Medical Search: SEO, AEO, and GEO Defined

The acronym confusion in healthcare marketing has real financial consequences. Practices that lump all visibility disciplines under "SEO" will continue treating symptoms while the disease, a structural shift toward answer synthesis, worsens.
AEO, or Answer Engine Optimization, is the discipline of structuring content so that an AI or voice assistant can extract and surface a single, clear answer to a patient's exact question. It replaces the question "will this rank?" with "does this page provide the clearest possible answer to the user's question?"
This is the layer that governs featured snippets, voice search results, and the standalone answers now dominating mobile medical queries. For a dermatology practice, this is the difference between a patient asking "does retinol work for acne?" and Google surfacing a 45-word response directly from your educational blog, without requiring a click.
GEO, or Generative Engine Optimization, is the meta-layer that determines whether generative AI systems synthesize your practice's information into their multi-source answers at all. It governs how legible your brand, your practitioners, and your content are to these AI systems when they construct answers from disparate data points. If your content doesn't follow GEO principles, systems like Google's AI Overviews, ChatGPT, or Perplexity will bypass your practice entirely.
The Verification Imperative: How E-E-A-T and YMYL Dictate Medical AI Visibility
Google's Search Quality Rater Guidelines treat medical content as YMYL, or Your Money or Your Life material, meaning any information impacting health decisions faces the platform's maximum threshold of scrutiny. The question is not whether your content is "good enough." The question is whether a Google quality rater or, increasingly, an automated SAFE classifier, can verify the source's credentials with zero ambiguity.
The E-E-A-T framework, Experience, Expertise, Authoritativeness, and Trust, is the sorting mechanism. For medical practices, Experience now means demonstrable clinical background. It requires explicit bios with credentials, board certifications, and institution affiliations on every medical content page, not buried on one "about" page. AI systems scan for entity-to-entity connections in a few key places: whether your practitioners appear in NIH-indexed research, whether your practice is listed in verified provider directories like Healthgrades, and whether your content's medical claims trace back to consistent, credentialed authorship.
Authoritativeness is signaled externally. AI synthesizers weigh third-party citations far above self-published claims, which is why a single mention in a peer-reviewed journal indexed by PubMed often carries more weight than a dozen optimized blog posts. The trust layer is where HIPAA compliance, transparent privacy practices, secure site signals, and accurate, current licensure documentation intersect to create the safety signal AI engines demand before citing any healthcare entity.
You cannot buy these signals. You can only build and publish them systematically across your site architecture, structured data, and external entity graph. The practices that will dominate AI-driven local search are those whose verification layer is visible, machine-readable, and continuously updated.
The Citation Economy: Why Third-Party Mentions Outrank Your Practice's Pages in AI
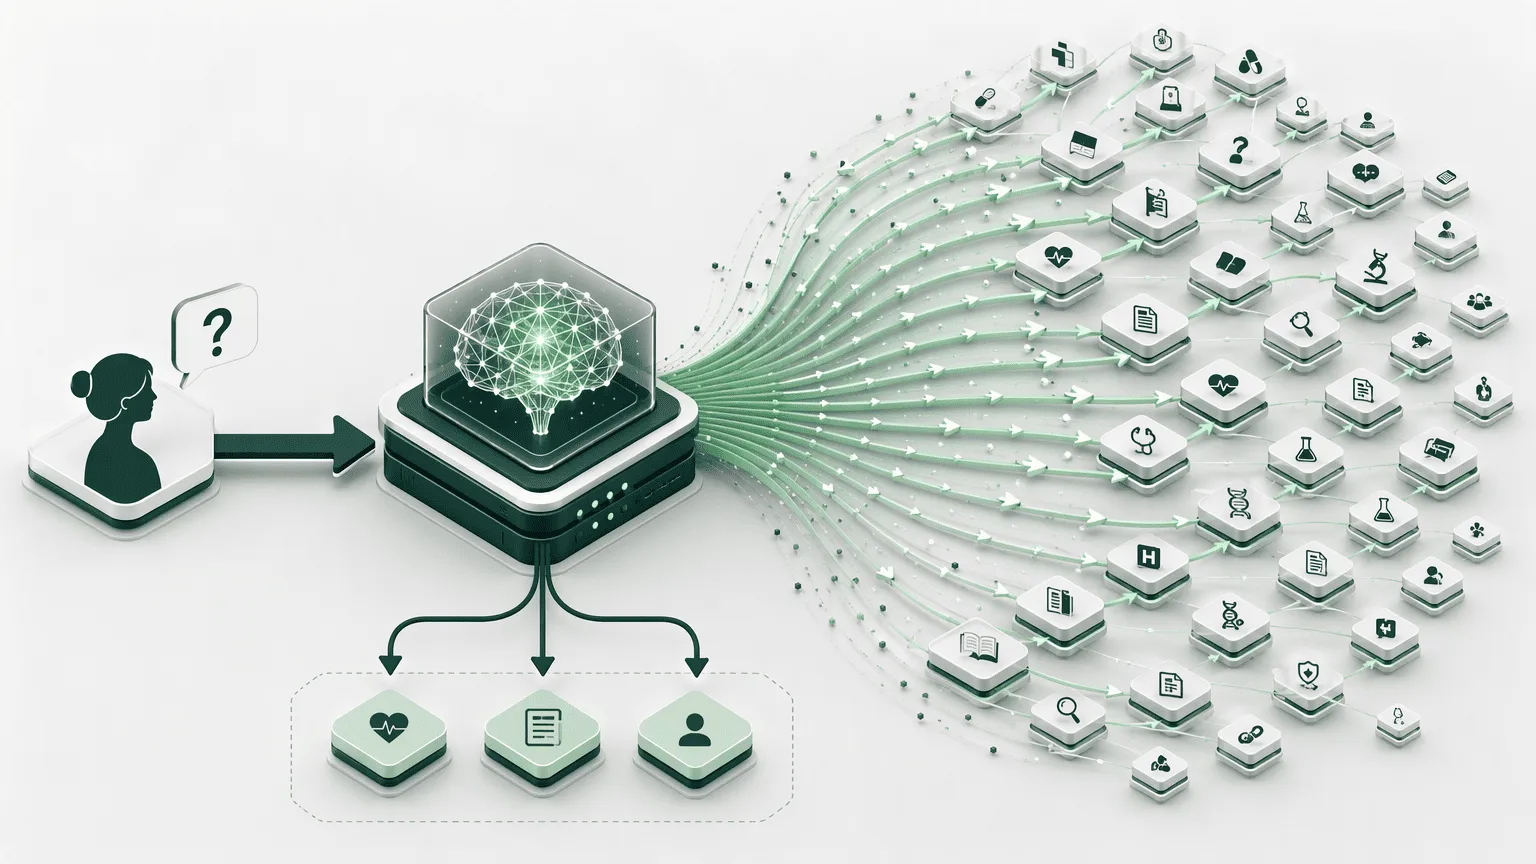
The single most uncomfortable finding in medical AI visibility research is that your owned content is not your primary acquisition engine. An analysis of 9 million AI answers across nine AI platforms and over 400 enterprise brands found that 82% of citations for bottom-of-funnel commercial prompts go to third-party sources, while owned pages represent just 3%. For healthcare, this means a patient asking "best cardiologist for arrhythmia near me" receives an AI-generated answer built predominantly from external directories, review sentiment, and third-party medical authority sites, not your service page.
The trade-off is real, but it is not fatal. Owned content that does get cited produces longer-lasting AI visibility because practices can continuously update, enrich, and republish it with new structured data. The strategy must therefore recalibrate to a citation-first posture, where directory management, review acquisition, and earned medical authority mentions receive at least equal investment as on-site publishing.
| Citation Source Type | AI Visibility Weight | Practical Control | Action Required |
|---|---|---|---|
| Third-party medical directories (Healthgrades, Zocdoc, Vitals) | High, primary AI triggers for local provider synthesis | Partial, verifiable listing accuracy, review recency, and structured data completeness are within your control | Audit and claim every major listing; maintain approximately 25 high-authority citations per location with consistent NAP data |
| Review platforms (Google Business Profile, RateMDs) | High, AI systems evaluate review quality, patterns, and sentiment as direct ranking factors | Partial, volume and recency can be accelerated ethically; specific text is patient-owned | Implement structured, HIPAA-safe review generation workflows across every visit type |
| Earned medical media (peer-reviewed journals, NIH-indexed research, medical news outlets) | Very high, citations from these sources produce the strongest entity-to-entity authority signals | Low, these require genuine clinical contribution and research output | Ensure all practitioner publications are structurally linked back to the practice via consistent schemas |
| Owned educational content (service pages, condition guides, blog) | Low as initial AI answer source; high as long-term trust sustainment | High, complete editorial, structural, and schema control | Restructure all medical content to answer-focused formats with clear author credentialing |
Constructing an AI-Citable Content Ecosystem Without Violating HIPAA

The central tension for medical marketers is that AI engines reward the precise, detailed, patient-question-driven content that HIPAA's Privacy Rule restricts whenever it involves protected health information (PHI). The fix is an architectural separation.
The HIPAA-compliant pattern that works for AI visibility separates your content into two strictly governed layers. The first is a public educational layer containing AI-optimized condition guides, procedure explainers, recovery timelines, and treatment comparison resources, all built from de-identified clinical knowledge and never from patient data. The second is a transactional/clinical layer behind authentication that handles scheduling, medical history, and PHI. The educational layer carries full structured data, author credentials, and citation signals. The transactional layer stays invisible to AI crawlers.
Content formats that perform well in AI synthesis while remaining HIPAA-safe include physician-authored condition overviews and "what to expect" recovery roadmaps with third-party outcome data citation. Equipment or modality comparisons framed around clinical applications rather than patient cases also work. You can use a platform like ClinAds to house and distribute this content with the compliant architecture already built into the system.
AI-Driven Reputation Engineering: From Review Generation to the 'Map Pack'
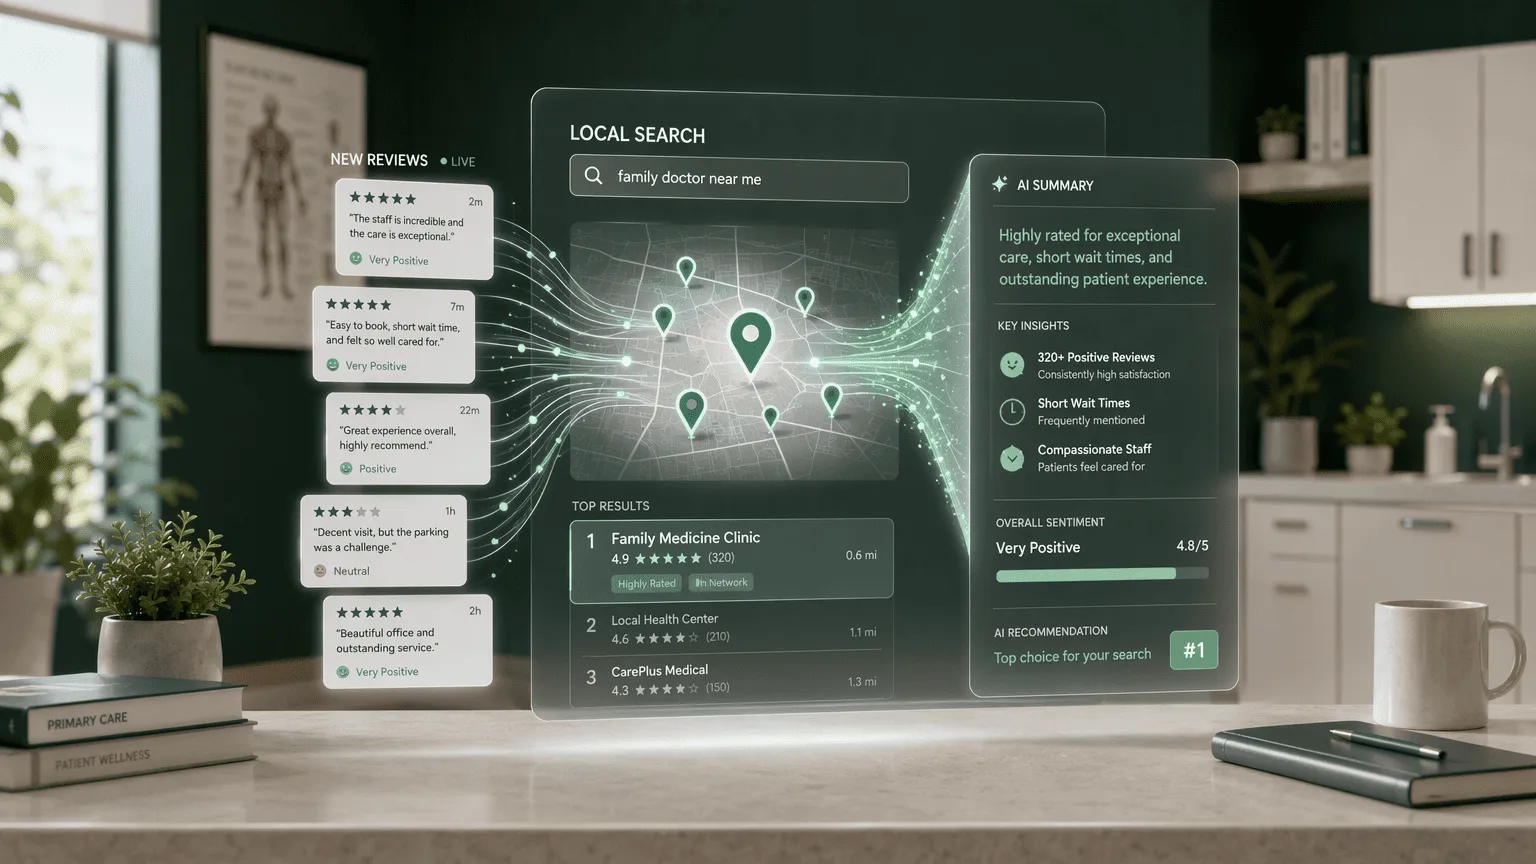
The traditional Map Pack is contracting and, on mobile, often disappearing behind AI Overviews that summarize provider recommendations directly. AI systems increasingly evaluate review quality, patterns, and sentiment as a direct ranking signal, meaning a practice with 47 recent, positive, detailed reviews will be cited over one with 200 stale, generic entries.
The implication is tactical: review recency and sentiment specificity now carry weight equal to volume. A two-sentence Google Business Profile review that names a condition, a specific procedure, and a practitioner will feed an AI synthesizer far more signal than a "great doctor" entry from three years ago. Practices must implement review generation workflows that invite this depth, following every completed visit type with timing that complies with medical board rules, which typically prohibit solicitation based on specific patient outcomes.
Google Business Profiles remain the single most important local SEO asset, but they only function as AI visibility triggers when managed as a living entity. This means weekly post updates, Q&A section monitoring, photo freshness, and direct response to every review. A dormant profile is a negative signal. An actively managed one broadcasts verification and trustworthiness to both patients and AI classifiers.
Tying AI Visibility to the Appointment Book: Metrics That Matter for Practices
Vanity rankings mean nothing if the scheduled patient count stays flat. The concrete metrics that close the attribution gap from AI visibility to booked revenue are specific, trackable, and actionable now. Here is the measurement framework to adopt:
- AI-overlay impression share: Track how often your practice appears specifically inside AI Overviews, ChatGPT-generated answers, and Perplexity synthesizations for your target condition and procedure queries. This is a separate metric from traditional organic SERP position and the single most important leading indicator of AI patient acquisition.
- Chat and click-to-call attribution from AI surfaces: Implement dynamic number insertion and session-based call tracking that differentiates calls generated from AI-sourced sessions versus standard organic traffic. A patient who reads your name in an AI summary and calls directly never shows up in standard conversion paths unless you instrument this one.
- New-patient appointment source tracking: Your EHR and scheduling system must capture the true origin, including "found through ChatGPT," "seen in AI answer," or "Google AI recommended," via intake form fields. Do not default these patients to "internet" or "search." AI-mediated discovery is a distinct acquisition channel.
- Benchmarking against traditional channels: Measure cost-per-new-patient and time-to-first-appointment separately for AI-acquired patients versus organic search, paid search, and referral. In early data patterns, AI-acquired patients often arrive with higher clinical specificity and shorter decision timelines because the AI system pre-qualifies them to your subspecialty.
The Compliance Guardrails: Licensing Board Rules and Google's SAFE System

State medical boards now scrutinize any patient-facing content an AI system might surface about your practice. Most state advertising regulations, including the Federation of State Medical Boards guidelines, cover content visible to prospective patients regardless of medium. AI-generated answers naming your practice fall squarely under that umbrella.
The most commonly triggered violations: unqualified specialization claims like "expert in" or "leader in," testimonials and before-and-after imagery published without the disclaimers state boards require, and claims that cannot be independently verified through board certification or peer-reviewed evidence. Google's Scaled Abuse Forensics Examiner, or SAFE, system is an automated large-scale abuse detection mechanism built to identify AI-generated medical misinformation and unsubstantiated health claims at scale. A SAFE flag can silently remove your practice's content from AI surfaces.
For practices, this creates two separate risks. A patient complaint about misleading content can trigger a state board investigation.
Separately, an algorithmic SAFE flag can erase your visibility in AI search results overnight. The defense is straightforward. Every health claim you publish on any platform needs a direct citation to verifiable, authoritative evidence.
Restrict all practitioner bios and specialization language to credentials you can produce a board certificate for. That rule applies everywhere your name might appear in a machine-generated answer.
Conclusion
The practices winning patient acquisition in 2026 have internalized three structural shifts. They treat external citation cultivation as a primary marketing function. They have separated HIPAA-safe educational content from transactional interfaces so AI engines have something legitimate to cite.
And they manage reputation, review velocity, and directory presence as direct AI ranking factors. This requires ongoing operational machinery.
AI search surfaces will continue expanding their footprint through 2027, and the practices that build systems to sustain verified, citation-rich, review-active presence will capture the majority of AI-mediated patient volume. The ones running the 2019 playbook will find ranking reports intact but waiting rooms empty.
Frequently Asked Questions
How can healthcare practices use AI to improve their local SEO and appear in the 'map pack' for patient searches?
AI visibility and Map Pack presence are no longer separate. Maintain an actively managed Google Business Profile with weekly posts, fresh imagery, and rapid review responses. Build approximately 25 consistent high-authority directory citations. And generate recent, specific patient reviews because AI systems now weigh review sentiment and recency as direct local-ranking signals.
What are the specific HIPAA compliance risks when using generative AI for healthcare content creation?
Entering PHI into a public generative AI tool creates an immediate breach. The architectural fix is to maintain two separate layers: public educational content built from de-identified clinical knowledge, and a protected transactional layer behind authentication. Never feed patient-specific data to train or prompt a publicly accessible AI content generator.
Which AI SEO tools are best suited for medical practices versus general business tools?
Medical practices need tools that handle structured entity data, healthcare directory management, and HIPAA-compliant content architecture, not just rank tracking. Specialty platforms like ClinAds provide GEO and review-generation workflows purpose-built for healthcare, whereas general tools lack the compliance guardrails and E-E-A-T-specific monitoring that medical visibility demands.
How does Google's E-E-A-T and YMYL framework affect AI-generated medical content in search rankings?
YMYL classification puts medical content under maximum scrutiny. Google's E-E-A-T framework requires demonstrable clinician credentials, verifiable author bylines, and external authority signals for any page to be cited in AI Overviews. Content lacking explicit, entity-linked medical authorship will not surface in AI-synthesized answers regardless of keyword optimization.
Can AI tools automate patient review management without violating healthcare regulations?
Yes, when designed for healthcare. Compliant tools can automate review request timing, direct patients to HIPAA-safe feedback flows, and monitor for review sentiment and platform coverage. They must never fabricate or edit reviews, and review solicitation must comply with state medical board rules, which typically prohibit soliciting reviews that imply specific clinical outcomes.
Sources
- Local SEO Services for AI-Driven Healthcare Search - healthcaresuccess.com
- SEO, GEO & AEO News: September 2026 Updates | LSEO - lseo.com
Want help executing this for your clinic?
Book a 30-minute call and we will map what a real ad engine would look like for your specific service mix.
Book a call